Executive Survey Insights  | Wave 8, Week Ending June 7, 2020

A NIC report providing timely insights from owners and operators on the pulse of seniors housing and skilled nursing sectors. Wave 8, week ending June 7.

A NIC report developed to provide timely insights from owners and C-suite operators and executives on the pulse of seniors housing and skilled nursing sectors.

NIC’s weekly Executive Survey of operators in seniors housing and skilled nursing is designed to deliver transparency into market fundamentals in the seniors housing and care space at a time where market conditions are rapidly changing—providing both capital providers and capital seekers with data as to how COVID-19 is impacting the space, helping leaders make informed decisions. 

This Wave 8 survey sample includes responses collected May 25-June 7, 2020 from owners and executives of 150 seniors housing and skilled nursing operators from across the nation. Detailed reports for each “wave” of the survey can be found on the NIC COVID-19 Resource Center webpage under Executive Survey Insights.


Join other operators in the sector and participate in the next wave.

{{cta(‘aab3162f-16e2-471f-86e4-d327039747dd’)}}


In an effort to balance the time commitment of operators responding to our surveys while simultaneously continuing to provide transparency through the delivery of timely and informative data during the COVID-19 pandemic, NIC is separating the existing Executive Survey Insights into two alternating surveys:

  • Executive Survey Insights: Market Fundamentals – Researches the impact of COVID-19 on occupancy rates, move-in and move-out rates, development pipelines, staffing, and supports for frontline community employees and staff.
  • Executive Survey Insights: COVID-19 – Provides insights into how COVID-19 penetration differs across care segments from both a cumulative and in-place perspective.

Surveys will be distributed on a staggered, every other week basis and the analysis of the survey responses will be made public on our website in the NIC Notes blog. Responses from both surveys will continue to be shared with survey participants in advance of public release. Additionally, the historical Executive Survey Insights can be accessed on the NIC COVID-19 Resource Center.

Wave 8 Summary of Insights and Findings

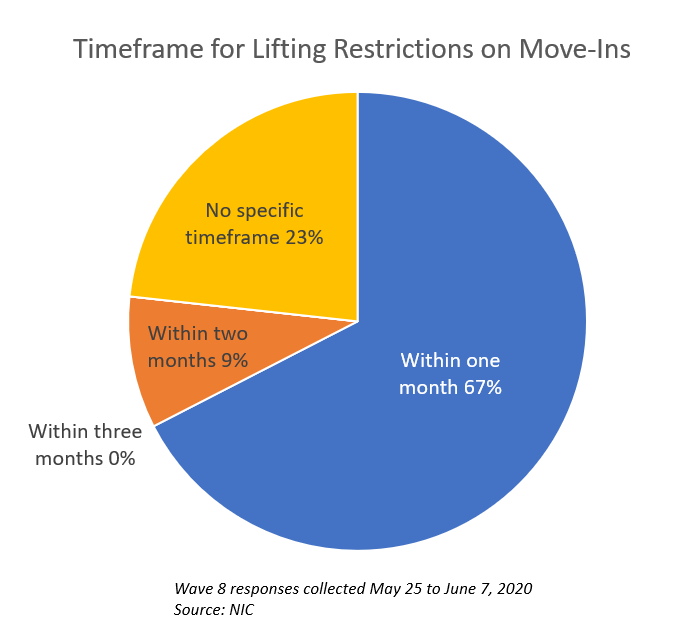
The pace of move-ins and move-outs improved across all segments, resulting in a smaller share of organizations reporting month-over-month and week-over-week declines in occupancy than in prior waves of the survey. Of those with bans on move-ins, either self-imposed or government-imposed, two of every three organizations anticipate lifting restrictions on move-ins within one month, while approximately one in four specified no time frame.

  • While most organizations continue to report a deceleration in move-ins in the past 30-days, in Wave 8 of the survey, the shares of organizations reporting deceleration is the lowest—across each of the care segments—since the first two waves of the survey (data collected March 24-31 and April 1-12). Furthermore, the shares of organizations reporting an acceleration in move-ins was the most of any wave to date.
  • Reasons cited for a deceleration in move-ins continue primarily to be slow leads conversions/sales resulting in difficulty replacing residents who have passed away or moved out. However, about 15% fewer organizations cite an organization-imposed ban on move-ins in Wave 8 compared to Wave 5, as all states have begun to loosen social and economic restrictions. About one-half of respondents continue to cite resident or family member concerns about moving in. Others continue to note fewer hospital referrals or elective surgeries that bring in residents for rehabilitation and therapy.
  • Fewer organizations saw a month-over-month decrease in occupancy compared to earlier survey waves. Additionally, the shares of organizations reporting an increase in occupancy from the prior month increased to the highest since the first two waves of the survey (between 14% and 25% in Wave 8). Respondents with independent living, assisted living, and memory care segment units report slightly higher shares of stable or improving occupancy rates from a week ago.
  • Approximately one in four organizations indicated that both access to PPE and access to COVID-19 testing kits has improved considerably, while 58% indicated it has improved somewhat for PPE and 47% for test kits. Roughly one in four organizations report that it is still difficult to obtain enough testing kits.


Wave 8 Summary Demographics

  • Responses were collected May 25-June 7, 2020 from owners and executives of 150 seniors housing and skilled nursing operators from across the nation.
  • Two-thirds of respondents were exclusively for-profit providers (66%), about one-quarter (27%) were exclusively nonprofit providers, and 7% operate both for-profit and nonprofit seniors housing and care organizations.
  • Owner/operators with 1 to 10 properties comprise 53% of the sample. Operators with 11 to 25 properties make up 25% while operators with 26 properties or more make up 22% of the sample.
  • Many respondents in the sample report operating combinations of property types. Across their entire portfolios of properties, 81% of the organizations operate seniors housing properties (IL, AL, MC), 34% operate nursing care properties, and 28% operate CCRCs (aka Life Plan Communities).


Key Survey Results

Pace of Move-Ins and Move-Outs

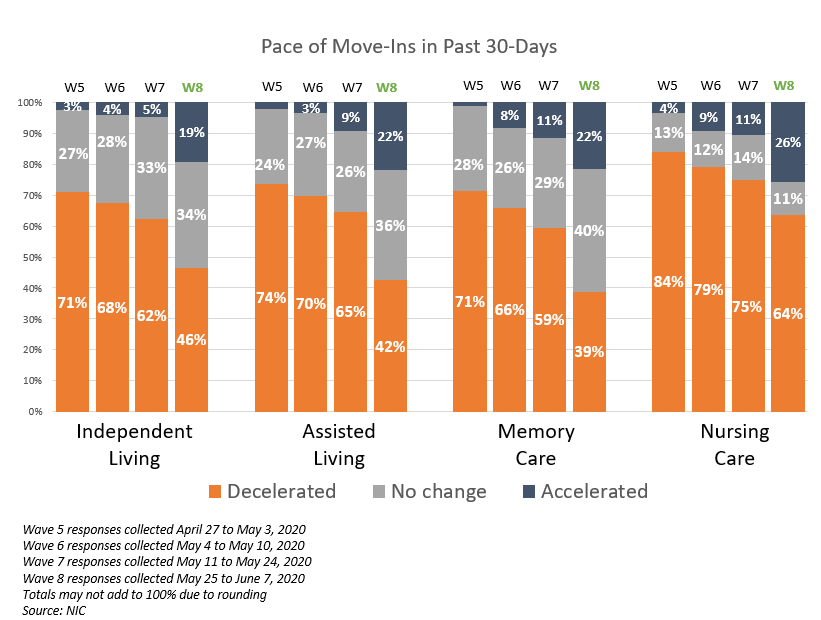
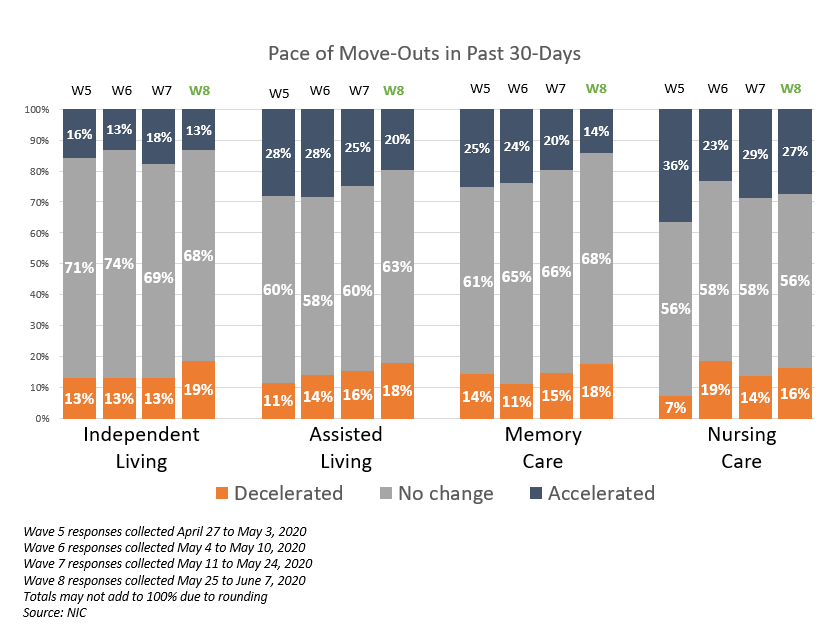
Respondents were asked: “Considering my organization’s entire portfolio of properties, overall, the pace of move-ins and move-outs by care segment in the past 30-days has…”

  • The shares of organizations reporting a deceleration in move-ins in the past 30-days is the lowest, across each of the care segments, since the first two waves of the survey (data collected March 24-31 and April 1-12), while the share of organizations reporting an acceleration is the highest.
  • In Wave 8 of the survey, between 39% to 46% of organizations reporting on their independent living, assisted living and memory care segments, and 64% of organizations with nursing care beds indicated that the pace of move-ins decelerated in the past 30-days—a continuing trend in improvement.
  • Additionally, approximately 20% of organizations with independent living, assisted living, and memory care segments and about one-quarter of organizations with nursing care beds saw an acceleration in move-ins in the past 30-days.
 

Reasons for Deceleration in Move-Ins

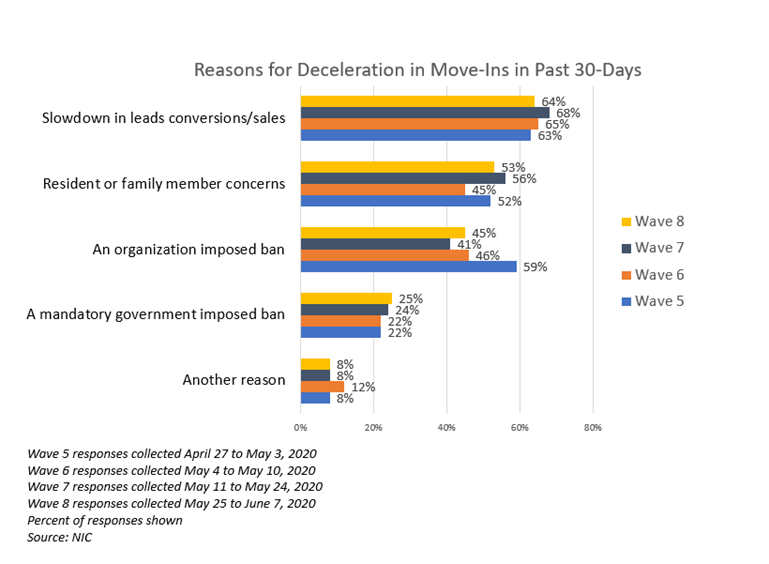
Respondents were asked: “The deceleration in move-ins is due to…”

  • Significantly fewer respondents in recent surveys cited an organization-imposed ban on settling new residents into their communities than in earlier waves (45% in Wave 8 versus 59% in Wave 5).
  • In Wave 8 of the survey—in similar proportions to the prior three waves—roughly two-thirds of respondents attribute a deceleration in move-ins to a slowdown in leads conversions/sales. Around one-half of organizations cite resident or family member concerns, and about one-quarter cite a mandatory government-imposed ban. Others cite fewer hospital referrals and elective surgeries that bring residents in for rehabilitation and therapy.
 

When Organizations Will Lift Restrictions on Move-Ins

Respondents that reported having an organization-wide ban or mandatory government-imposed ban were asked: “My organization anticipates lifting restrictions on settling new residents into some or all of our communities…”

  • In Wave 8, two of every three organizations anticipate lifting restrictions on move-ins within one month, while approximately one in four specified no timeframe.
Move-Outs

  • Between 63% and 68% of organizations reporting on their independent living, assisted living, and memory care units in Wave 8 saw no change in move-outs in the past 30-days, similar to Wave 7, while approximated 20% reported decelerations.
 

Change in Occupancy by Care Segment

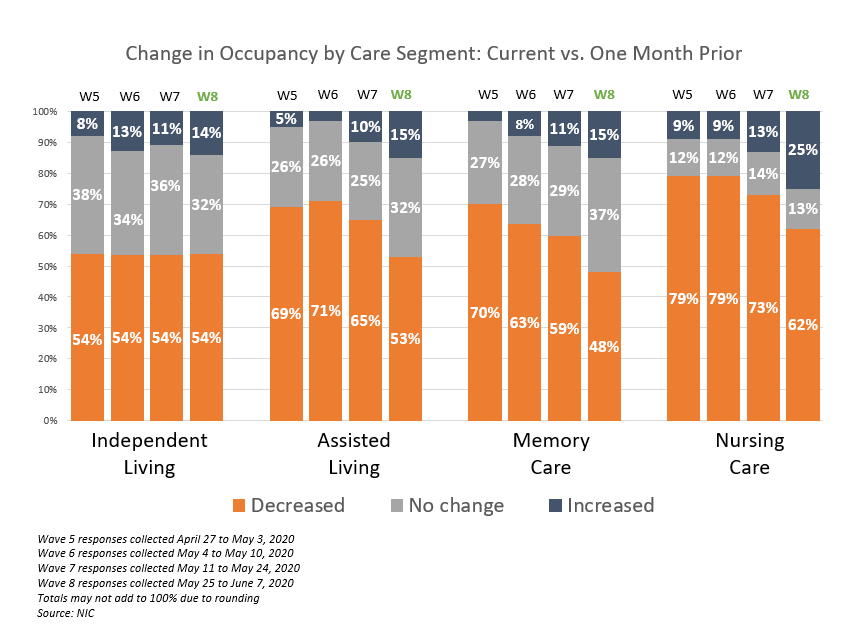
Respondents were asked: “Considering the entire portfolio of properties, overall, my organization’s occupancy rates by care segment are… (Most Recent Occupancy, Occupancy One Month Ago, Occupancy One Week Ago, Percent 0-100)”

  • Approximately one-half of organizations reporting on their independent living, assisted living, and memory care units in Wave 8 of the survey—across their respective portfolios of properties—experienced a decrease in occupancy from the prior month, while roughly one-third report no change (32% to 37%).
  • Notably, one in four organizations with nursing care beds reported an increase in occupancy from the prior month, and 14%-15% of organizations with independent living, assisted living units or memory care units report an increase in occupancy in the past month. This was the highest since earlier waves of the survey.
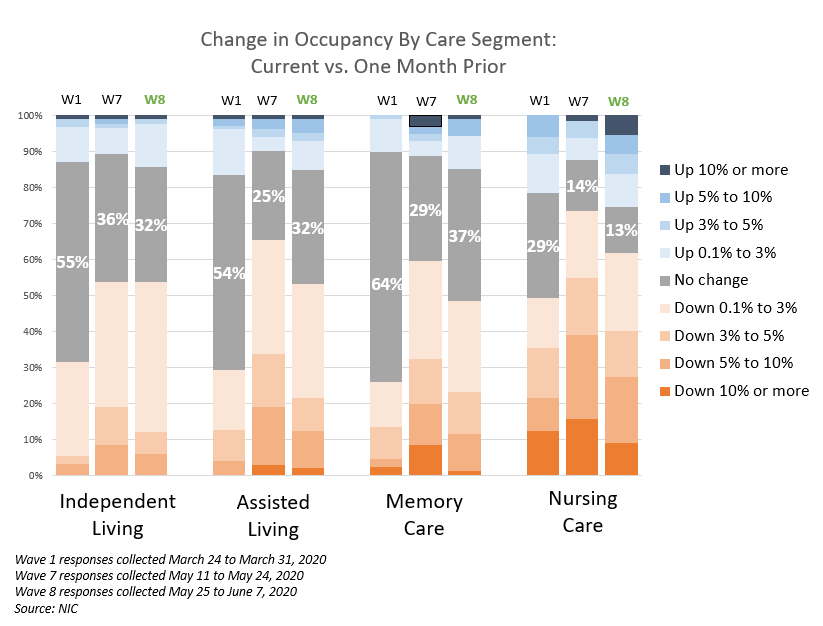
  • The chart below breaks out the rates of change in occupancy by care segment with greater granularity, comparing the current timeframe (Wave 8 data collected between May 25 to June 7), to the prior survey (Wave 7 data collected between May 11 and May 24), and earlier in the pandemic at the start of this survey when the majority of independent living, assisted living and memory care segments had yet to report major changes in current occupancy compared to one month prior (Wave 1 data collected between March 24 and March 31).
  • As shown in the chart, near the beginning of the pandemic (Wave 1), the share of operators that reported month-over-month occupancy rate declines increased as the pandemic progressed. More recently in Wave 8, the share reporting downward changes in occupancy has declined for all segments but independent living. The majority of those reporting occupancy declines in independent living reported declines between 0.1% and 3.0%.
  • Regarding the change in occupancy from one week ago, respondents with independent living units consistently report the fewest declines in occupancy from one week earlier while assisted living and memory care saw fewer organizations reporting declines (27%, respectively) than in prior surveys.
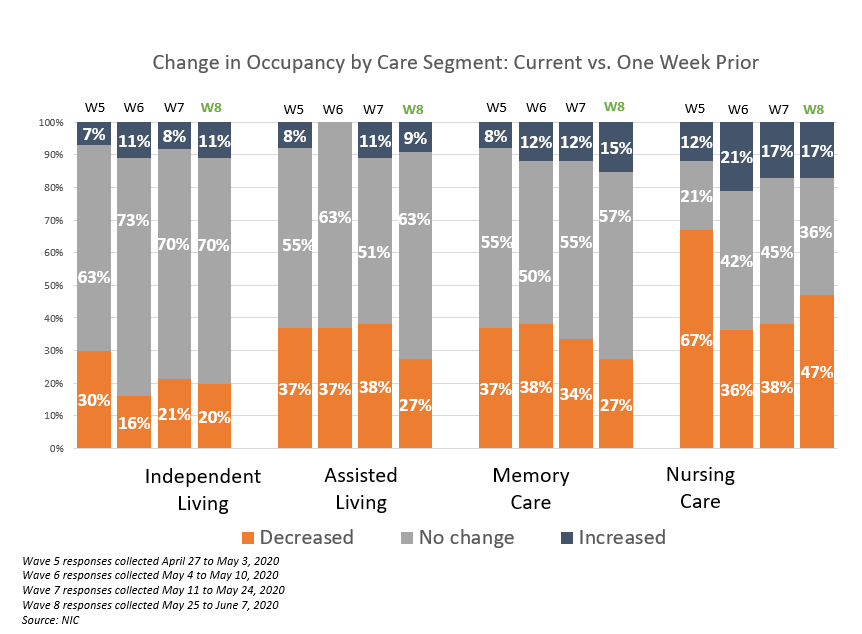
 

  • Most organizations with independent living, assisted living and memory care segment units note no change (57% to 70%); however, slightly higher shares of organizations with independent living and memory care segment units report an increase in occupancy from one week ago. Organizations reporting on nursing care beds reported the highest share of higher occupancy rates from the prior week (17%), the same as in Wave 7.


Improvement in Access to PPE and COVID-19 Testing Kits

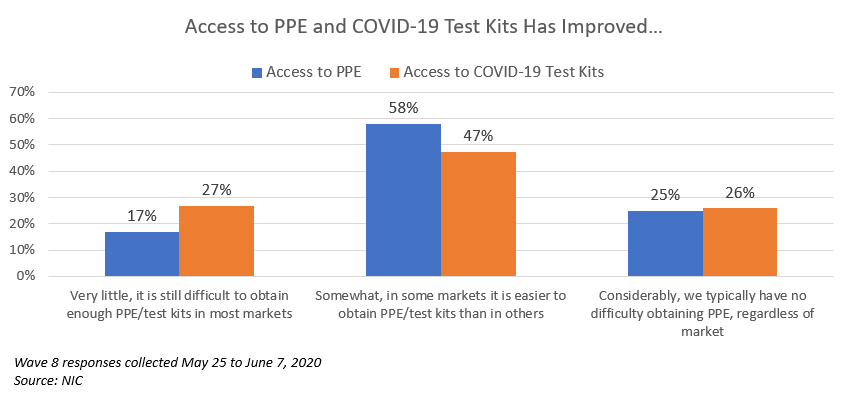
Respondents were asked: “Considering access to PPE (personal protective equipment) and COVID-19 testing kits, my organization has experienced that access has improved…”

  • Approximately one in four organizations responding to this inquiry indicated that both access to PPE and access to COVID-19 testing kits has improved considerably, while 58% indicated it has improved somewhat for PPE and 47% for test kits. Roughly one in four organizations report that it is still difficult to obtain enough test kits.
NIC wishes to thank survey respondents for their valuable input and continuing support for this effort to bring clarity and transparency into market fundamentals in the seniors housing and care space at a time where trends are rapidly changing. NIC also thanks both ASHA and Argentum for their support in encouraging participation in the Executive Survey Insights: COVID-19 survey. The results of our joint efforts to provide timely and informative data to the market in this challenging time have been significant and noteworthy.

The Executive Survey Insights: COVID-19 survey is now open. To respond to the survey, please click here.

If you are an owner or C-suite executive of seniors housing and care properties and have not received an email invitation but would like to participate in the current Executive Survey, please send a message to insight@nic.org to be added to the email distribution list.


{{cta(‘6d369449-a2fa-4e14-bab5-436c566fb4b4’)}}

NIC MAP Releases the First Intra-Quarterly Data Set

NIC has launched initiatives to provide seniors housing data on an accelerated timetable, and announces the release of NIC MAP® Intra-Quarterly Data.

The COVID-19 pandemic has created an urgency for insights on data and trends in the seniors housing and care sector. NIC has long held that transparency, accuracy, and timeliness are key factors for well-informed decision-making.In response to the quickly developing situation presented by COVID-19, therefore, NIC has launched a number of initiatives to provide relevant data on an accelerated timetable, including last week’s release of NIC MAP® Intra-Quarterly Data.

The NIC MAP Data Service team, working with diligence and passion, has produced a new monthly time series. The April data, released May 19, marks the inauguration of the new NIC MAP Intra-Quarterly Data series. 

Monthly Reporting of NIC MAP Data

With the launch of Intra-Quarterly Data, the NIC MAP Data Service will now report three-month rolling time series data on a monthly basis. The data represents performance for the three most recent months, labeled as the final month for the reported period. The rolling period for April 2020 covers February, March, and April 2020. This first data release includes 13 months of three-month rolling data on stabilized occupancy for both seniors housing and nursing care properties. The data series begins in April 2019 and is reported for the Primary Markets, Secondary Markets, and other aggregated geographic levels. 

The NIC MAP Intra-Quarterly Data will be delivered as an Excel file for NIC MAP clients and will also be featured in NIC’s Intra-Quarterly Snapshot, a new monthly publication offering highlights from the data. The Intra-Quarterly Snapshot, available for download on NIC.org, includes key takeaways on the reported time series data, visual representations, and statistics for the past 13 rolling three-month periods, plus three economic indicators to provide some perspective on the current economic conditions. 

Note that the publishing of the Intra-Quarterly Data and Intra-Quarterly Snapshot report will occur on the third Tuesday of each month. 

April 2020 Intra-Quarterly Data Key Takeaways 

In April 2020, following the onset of the COVID-19 pandemic, stabilized occupancy for both seniors housing and nursing care properties dropped significantly. Nursing care properties experienced the largest decline, falling 220 basis points from the prior month to 84.7% for the rolling period of February-March-April 2020 in the NIC MAP Primary Markets. The seniors housing stabilized occupancy rate fell a lesser 110 basis points over the prior month to 88.7% for the NIC MAP Primary Markets. Prior to April, both the seniors housing and skilled nursing stabilized occupancy rates had been relatively stable. 

The impact of COVID-19 was clearly reflected in the rolling period of April 2020, with a greater toll seen in skilled nursing than in seniors housing. Specifically, the drop in stabilized occupancy for both skilled nursing and seniors housing is indicative of the effects of the pandemic on existing properties without the effects of competition of new properties on market conditions.  In addition, some of the sharp decline in skilled nursing occupancy was likely driven by fewer hospitals discharging patients to post-acute care settings for rehabilitative therapy as hospitals defer elective surgeries due to the pandemic.

More to Come

Going forward, NIC will continue to expand the NIC MAP Intra-Quarterly Data set and report on additional metrics, geographies, and data subsets in the third quarter of 2020.

In the meantime, NIC will continue to respond to the pandemic by doing what we do best − delivering data, analytics, and connections – to continue to provide transparency to the sector. Details can be found on our COVID-19 Resource Center which puts new data initiatives, as well as COVID-19-relevant commentaries, regulatory updates, and popular webinar details all in one place.

NIC would like to recognize those directly impacted by the COVID-19 pandemic and those on the frontline keeping residents of seniors housing and skilled nursing communities safe. We understand that seniors housing and skilled nursing operators are bearing tremendous burdens, and applaud their efforts to protect and serve their residents.

Telehealth Embraced as a Result of COVID-19 Pandemic

The COVID-19 pandemic has ushered in an era of unprecedented change in the world’s healthcare landscape.  Some of these changes may be temporary – lasting only until a vaccine or widespread testing is available – but others will have secured their place with consumers and will become permanently woven into the fabric of the healthcare […]

The COVID-19 pandemic has ushered in an era of unprecedented change in the world’s healthcare landscape.  Some of these changes may be temporary – lasting only until a vaccine or widespread testing is available – but others will have secured their place with consumers and will become permanently woven into the fabric of the healthcare system. There is an increased sense of uneasiness in visiting medical office buildings, urgent care sites, and hospitals, especially for routine checkups and minor ailments. Despite this apprehension, the level of care needed to support the United States’ population has not subsided.

It is a real concern that people may be deferring or delaying preventive care and physician visits out of a fear of getting infected, potentially allowing problems to remain undetected and untreated. In lieu of face-to-face health visits, telehealth has stepped in to bridge the gap, as individuals can now increasingly use interactive apps with audio and video capabilities to visit with their clinician for a broad array of services.

CMS Regulatory Changes Encourage Telehealth Adoption

CMS (Centers for Medicare and Medicaid Services) is taking aggressive regulatory action to allow for the rapid implementation and expansion of telehealth programs. Among these actions is a series of waivers intended to break down barriers so that patients can access these services and to ensure that providers are reimbursed for them. These actions are currently intended to remain in effect only during the coronavirus public health emergency. One can easily imagine that a tipping point may be reached during the pandemic, where telehealth is proven to be a viable solution to health needs and is ultimately embraced as fully in a post-COVID world as it is being embraced currently.

Prior to these waivers, health care professionals could only bill Medicare fee-for-service for patient care delivered by telehealth if the established-relationship rule was met, meaning the patient had been to an in-person, face-to-face visit with the provider at least once in the prior three years. CMS has clarified that the established-relationship rule will not be enforced during the state of public emergency.  Medicare’s originating site rule has also been waived, meaning that instead of providers needing to be in a medical office, community clinic, hospital, stroke unit, dialysis center, or other more traditional healthcare delivery site, providers can virtually treat patients from anywhere – including their home.

CMS is also temporarily breaking down state boundaries to allow providers to practice across state lines, giving patients in rural areas improved access to telemedicine while simultaneously preserving the nation’s frontline medical staff. Such measures are encouraging the utilization and adoption of telemedicine and preventing the spread of coronavirus.telehealth for elderly resident of senior housing

What’s been made clear with the changes in the telemedicine regulatory environment is that CMS believes this practice is a viable channel for delivering care, if a patient’s condition doesn’t require more intensive hospital care. For routine physicals, prescription refills, and other minor ailments, telemedicine is a preferred conduit for obtaining care. What was intended to be a temporary measure during a public health emergency may have cemented a role in the future of our nation’s healthcare.

Benefits of Telemedicine Implementation

The COVID-19 pandemic has resulted in an extraordinary adoption in telemedicine by providers and patients alike and there’s no doubt that there are general benefits to expanded telehealth programs. Certainly, there is a convenience factor for patients who no longer experience long waits in a physician’s office waiting room. For frail elders and residents of seniors housing properties, however, the benefits are even greater. Those with a high risk of falling no longer need to hesitate when making appointments for fear of navigating parking structures and medical offices. Patients can rest easier knowing they can avoid potential exposure as telemedicine can connect them to specialized medical expertise to determine if they really require that trip to the hospital.

Residents of seniors housing and care properties that have established telemedicine programs are also able to rely on the expertise of on-site staff to use the remote equipment appropriately. For routine physicals and checkups, having an audio/visual connection will often suffice. But for more complex health problems, on-site staff are available to properly use the cameras, otoscopes, and stethoscopes that are making telemedicine technologies so robust. Having the staff onsite to assist with these remote office visits is delivering improved care to residents. Without this assistance, providers would not have access to the real-time vital signs and patient images that allow them to deliver high-quality care.

Establishing Telemedicine Programs in Seniors Housing and Care

Seniors housing and care providers had begun to experiment with telemedicine even before the coronavirus and COVID-19 pandemic became our reality. But in the new world we are living in, the pace at which properties are adopting and accepting this new form of care delivery is rapidly increasing.

Winter Park, Florida’s Holiday Retirement, the largest independent senior living provider in the U.S. announced in March that it has provided telehealth access and services to the residents of its 250+ senior living communities for urgent care situations and other conditions from the safety and comfort of their home. Senior leadership with Holiday indicated that partnering with MeMD’s national network of healthcare providers was in part a way to provide convenient care to residents, but also a larger strategy to reduce the stress on the United States’ healthcare delivery system. In the recently released Q1 2020 earnings report, Sabra Health Care REIT CEO Rick Matros commented that Holiday Retirement had done an effective job keeping infections low in their independent living buildings, in part due to the valuable rollout of their telemedicine program.Hh

Glendale, California-based senior living provider Front Porch Retirement Communities is working to expand the telehealth programs within the variety of senior living options they offer. As Kari Olson, chief innovation and technology officer indicates, “Any expansion of telehealth services is a very good thing, especially during this time when we need folks to stay home, and in particular, to safeguard people over 65 as well as other high-risk individuals.” Front Porch has been a proponent of telehealth for years, believing that telemedicine reduces barriers to accessing care, such as travel time and transportation risks.

Whether seniors housing and care providers are entering the world of telemedicine as a result of our new reality or they are expanding an already established telemedicine program, one thing is clear: telemedicine is proving itself to be a valuable aspect of care delivery in this country.


Record Decline of 20.5 million Jobs in April, As Stay at Home Orders Cause Massive Job Losses

Initial Jobless Claims Lower, but Still Nose-bleedingly High

The Labor Department reported that there were a nose-bleedingly high 20.5 million jobs lost in April as the COVID-19 pandemic closed much of the economy and triggered massive layoffs and furloughs of employees by U.S. businesses. This dwarfed the previous record high job loss of 1.96 million jobs in 1945 at the end of WWII and the 8.7 million jobs lost during the entire last recession. Employment is now at its lowest level since February 2011. April’s decline also marked the second monthly decline in jobs after a record 113 consecutive months of job gains.  


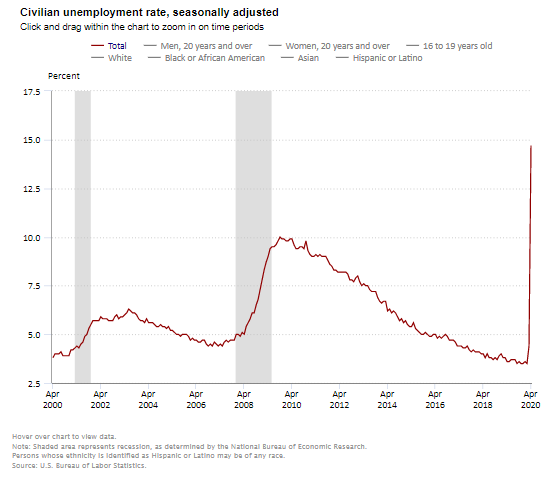
Separately, the April unemployment rate surged to 14.7%, up from 4.4% in March and from a 50-year low of 3.5% in February. This is the highest jobless level since the Great Depression according to the Labor Department figures that date back to the 1940s and the National Bureau of Economic Research data prior to that. During the 2008/2009 recession, the unemployment rate peaked at 10%.

The underemployment rate or the U-6 jobless rate soared to 22.7% in April from 8.7%. This figure includes those who have quit looking for a job because they are discouraged about their prospects and people working part-time but desiring a full work week. In the previous 2008/2009 recession, this rate peaked at 17.2%.

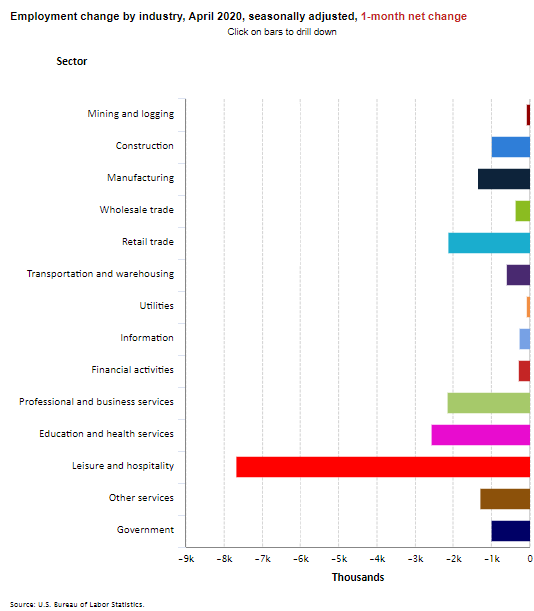
Employment fell sharply in all major industry sectors, with particularly heavy job losses in leisure and hospitality. Employment in health care fell by 1.4 million in April. The decline in healthcare reflects those not working to fight the pandemic because they are seeing fewer patients for routine checkups and, in some cases, only offering emergency procedures.

Revisions also subtracted thousands of jobs in the prior two months. The change in total nonfarm payroll employment for February was revised down by 45,000 from a gain of 275,000 to a gain of 230,000 and the change for March was revised down by 169,000 from a loss of 701,000 to a loss of 870,000. Combined, 214,000 jobs were subtracted to the original estimates. Monthly revisions result from additional reports received from businesses and government agencies since the last published estimates and from the recalculation of seasonal factors.

Average hourly earnings for all employees on private nonfarm payrolls rose in April by $1.34 to $30.01, a 7.9% increase from year-earlier levels. The increases in average hourly earnings largely reflect the substantial job losses among lower-paid workers, which put upward pressure on the average hourly earnings estimate.

The labor force participation rate, which is a measure of the share of working age people who are employed or looking for work fell 2.5 percentage point to 60.2%. Total employment, as measured by the household survey fell by 22.4 million to 133.4 million.

Separately yesterday, the Department of Labor reported that 3.2 million Americans filed for unemployment insurance benefits in the week ending May 2, 2020. In the past seven weeks, 33 million people have filed claims.

Today’s report was not unexpected as the pandemic has dramatically halted economic activity across the nation and globe. The question becomes how long the devastation will continue, which in turn largely depends on COVID-19 related factors such as when a vaccine become available, testing of the general population and when business are able to reopen. Even then while some businesses may gradually return to “normal”, not every sector will recover at the same pace. In the meanwhile, and tragically, millions of people are suffering from illnesses, anxieties and deaths associated with the pandemic and from the human tragedies associated with of the collapse in the national and global economies.

Pandemic Heightens Need for Middle-Market Housing

Care collaboration offers solution for the ‘Forgotten Middle.’ Collaboration among various stakeholders will likely play a significant role in securing affordable housing and appropriate care for middle-income seniors—a big group expected to increase in size in the wake of the COVID-19 pandemic. Medicare Advantage plans, adaptive re-use of commercial properties and telehealth are some of […]

Care collaboration offers solution for the ‘Forgotten Middle.’

Collaboration among various stakeholders will likely play a significant role in securing affordable housing and appropriate care for middle-income seniors—a big group expected to increase in size in the wake of the COVID-19 pandemic.

Medicare Advantage plans, adaptive re-use of commercial properties and telehealth are some of the vehicles that could be leveraged to create new approaches to house and care for middle-income seniors.

“Our nation’s middle-market seniors need a sustainable housing solution that addresses their projected health and wealth characteristics,” said NIC Chief Economist Beth Mace. “Given the COVID-19 pandemic, the need is only going to get bigger.”

NIC first identified the growing number of vulnerable middle-income seniors last year in its report, “The Forgotten Middle: Middle Market Seniors Housing Study.” It showed that 54% of seniors cannot afford today’s senior housing product—based on a monthly cost of $4,500—and do not qualify for assistance under the Medicaid program. By 2029, 14 million seniors will fall into that category.

That number will likely grow because of the pandemic and its economic fallout.

Seniors whose savings are depleted by the economic downturn will likely join the middle-income ranks of those who can’t afford the housing and care they need. And more of today’s middle-income could fall into the low-income category of elders who rely on Medicaid, stretching an already overburdened system.

Added to that, consumer confidence will take a hit, said Mace. A rocky stock market and big job losses create uncertainty which can impact decisions to move into seniors housing.

The problem of how to house the rising number of middle-income seniors, many with functional limitations, will be solved in part by an increase in care collaboration.

New approaches were discussed at the NIC Spring Conference during a session titled, “Planning for the Care Needs of the Forgotten Middle.”

Much of the discussion focused on how to integrate healthcare into housing.

“The middle market is where health and housing intersect,” noted Caroline Pearson, senior vice president at NORC, at the University of Chicago. She is co-author of the original ‘Forgotten Middle’ study.

Medicare Advantage insurance plans could help, session participants agreed. These plans, held by a growing number of seniors, are beginning to offer wraparound services such as payments for food, assistance with the activities of daily living and on-site healthcare.

Some senior living providers are forming their own Medicare Advantage plans while others are aligning with healthcare providers.

The big healthcare REIT Welltower, for example, formed a partnership with CareMore Health, a division of Anthem insurance. CareMore enrolls residents in Medicare Advantage plans. They are treated on-site by CareMore healthcare professionals.

“Senior living should be the convener of healthcare,” said session participant Kevin O’Neil, chief medical officer at Affinity Living Group. He added that on-site healthcare can help avoid costly emergency room visits. It’s easier on the resident too.

Working with local health systems is a priority, session participants agreed. But managed care organizations will only partner with senior living providers that can track outcomes, said Diane Burfeindt, vice president of population health at Presbyterian Senior Living. “Data is huge.”

Panelists presented other ideas to lower costs for middle-income seniors. Unused properties, such as vacant schools, could be converted into senior living properties. The low-cost basis of the property would help keep rents in check.

Government programs such as low-income housing tax credits and the rental of ground floor space to retailers are other cost-saving ideas. “It will take a multi-industry mindset,” said James Lydiard, general manager of CareMore’s Touch program for senior living communities.

Technology will help lower costs. Senior living providers are already stepping up their use of telehealth in the wake of the pandemic. Timely, virtual doctor visits will help maintain the health of middle-income seniors at an economical price. “Telehealth is the way to go to reduce the cost curve for the middle market,” said Mace.